Thecal sac as the cauda equina surrogate
Below the cord there is no cord. What you contour instead changes the constraint, and contouring the nerve roots individually is not reproducible.
Built in·updated 2026-08-20
Below roughly L1 the spinal cord has become the cauda equina, and the dose-limiting structure is a bundle of nerve roots, not a cord. That leaves a contouring choice, and the choice changes the number:
- the whole spinal canal — safest, most conservative, largest volume;
- the cauda equina only;
- the cauda equina with bilateral nerve roots.
Consensus has moved to the thecal sac as the practical surrogate, because it is a reproducible structure on CT and MR while individual nerve roots are not. Contour-variability work found exactly that: observers agree on the sac and disagree on the roots.
Why it matters on a scored case. A D0.03cc on "CaudaEquina" is a different number depending on which of the three someone drew, and the planner submitting has no way to know which was used unless the case says so. If you are contributing a spine case, say which convention you used; if you are planning one and it is not stated, that is a data issue worth raising rather than guessing.
Planning consequence. The gradient you need is in the 2–4 mm between the vertebral body target and the sac. That is why spine SABR is a fall-off problem rather than a coverage problem, and why the fall-off skills are the ones that pay here.
How the structure is built
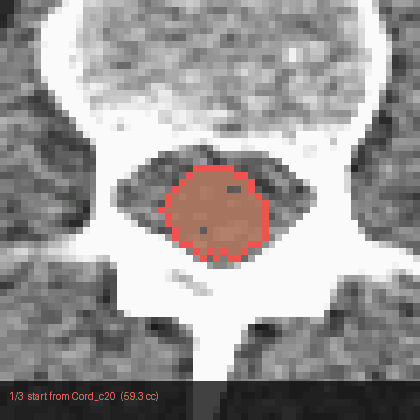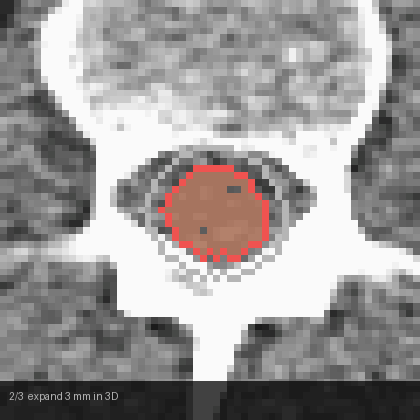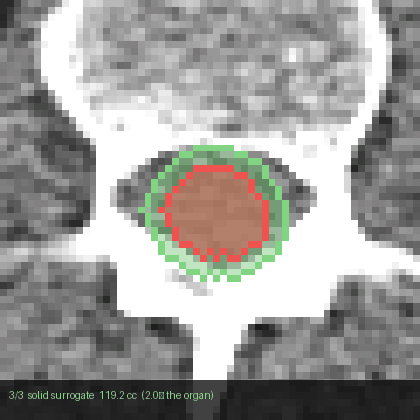
Where the numbers come from
- Thecal sac contouring as a surrogate for the cauda equina and intracanal spinal nerve roots for spine SBRT: contour variability and recommendations for safe practice
Int J Radiat Oncol Biol Phys · 2021
Observers agree on the thecal sac and diverge on individual nerve roots
- Stereotactic body radiation therapy to the spine: contouring the cauda equina instead of the spinal cord is more practical as the organ at risk
Rep Pract Oncol Radiother · 2023
Three contouring conventions compared: whole canal, cauda equina, cauda equina with roots